Central centrifugal cicatricial alopecia, or CCCA, is an inflammatory form of scarring hair loss that often begins around the crown. It can permanently destroy follicles, but prompt diagnosis and treatment may protect follicles that are still alive and sometimes allow meaningful regrowth from those areas.
Persistent crown breakage, burning, itching, tenderness, expanding thinning, or smooth scalp deserves a dermatologist’s attention. Oils, supplements, minoxidil, and hopeful bathroom-mirror negotiations cannot confirm CCCA or control active scarring on their own. (American Academy of Dermatology Association [AAD], n.d.-a)
Could This Be CCCA, or Something Else?
Crown thinning can look deceptively similar across several conditions. The location matters. So do scalp sensations, timing, follicular openings, styling tension, shedding pattern, and what happened a few months before the change began.
Use this as a conversation starter, not a home diagnosis.
|
What you notice |
What it may suggest |
Sensible next action |
|
Gradual crown thinning with itching, burning, soreness, tenderness, or breakage |
CCCA deserves consideration, though other conditions can look similar |
Arrange a dermatology appointment promptly |
|
Smooth or shiny scalp with fewer visible follicular openings |
Possible established scarring |
Do not rely on home treatment alone |
|
Thinning near the temples, hairline, or other areas exposed to repeated pulling |
Traction alopecia may be present |
Remove painful tension and seek assessment if loss persists |
|
Diffuse shedding after illness, childbirth, rapid weight loss, surgery, or severe stress |
Telogen effluvium may be more likely |
Review triggers and seek medical care if shedding is severe, prolonged, or accompanied by crown changes |
|
Pus, drainage, marked crusting, fever, boggy swelling, or painful nodules |
Infection or another inflammatory scalp condition may be present |
Seek prompt medical assessment |
More than one condition can occur on the same scalp. CCCA may coexist with female pattern hair loss, traction alopecia, seborrheic dermatitis, or diffuse shedding. That overlap is one reason treatment can disappoint when somebody starts with a product rather than a diagnosis.
And yes, checking your own crown is absurdly inconvenient. A phone camera, a second mirror, or one patient person can help. Otherwise, you may spend ten minutes twisting like a confused flamingo and still photograph the ceiling fan.
What Does CCCA Mean, and Why Can It Cause Permanent Hair Loss?

CCCA is a primary scarring alopecia. Inflammation damages hair follicles, classically beginning near the crown, and may eventually replace them with fibrous tissue. Hair may return from follicles that remain viable. A follicle already replaced by scar tissue cannot simply be coaxed back into normal function.
What Does the Name “Central Centrifugal Cicatricial Alopecia” Mean?
The name sounds like something that requires a clipboard and three years of Latin. Broken down, though, it describes the condition’s classic pattern:
- Central refers to the central scalp, especially the crown or vertex.
- Centrifugal means the affected area often spreads outward from that central point.
- Cicatricial means scarring.
- Alopecia is the medical term for hair loss.
CCCA is considered a primary scarring alopecia because the disease process directly targets the hair follicle. In secondary scarring alopecia, follicles are innocent bystanders damaged by another event, such as a burn, severe infection, radiation injury, trauma, or destructive skin disease.
The name is helpful. It is not a rigid dress code.
A 2024 scoping review found that CCCA can also appear in patchy, frontal, temporal, parietal, and occipital patterns. Some cases do not begin as a tidy circle in the middle. Others resemble female pattern hair loss or occur in several separated patches.
So, a crown-centered pattern raises suspicion, but an atypical distribution does not automatically rule CCCA out.
The older term hot-comb alopecia is now considered inadequate because it assumes a cause that has never been proved for every patient. CCCA occurs in people who have never used a hot comb or chemical relaxer.
What Happens Inside an Affected Hair Follicle?
A hair follicle is not merely a pore with a strand poking through it. It is a small, biologically active organ with structures responsible for growth, cycling, lubrication, and regeneration.
In CCCA, inflammation often develops around the upper follicle. This area includes the bulge region, which houses epithelial stem cells needed to renew the follicle during future growth cycles. When that regenerative area is repeatedly injured, the follicle’s repair capacity can be lost.
Microscopic changes may include:
- Lymphocytic inflammation around follicles
- Concentric perifollicular fibrosis
- Reduced or absent sebaceous glands
- Premature desquamation of the inner root sheath
- Follicular dropout
- Fibrous tracts where functioning follicles once sat
Premature inner-root-sheath desquamation can support the diagnosis, but it is not exclusive to CCCA. The pathologist has to interpret it alongside the clinical pattern, symptoms, trichoscopy, and other tissue findings.
As fibrosis advances, normal follicular openings may become difficult to see. The scalp may look smoother or shinier. By then, some follicles may already be gone.
That distinction matters enormously. An inflamed follicle may still be salvageable. A fibrous tract is not a sleeping follicle. It is the remnant of one.
The remaining follicles are the reason treatment matters.
CCCA should not be presented as a circulation problem. Increased blood flow has not been established as its cause, nor as the central mechanism required to reverse the disease. The pathology is primarily inflammatory and fibrotic, not a matter of insufficient scalp “delivery.”
Who Is Most Often Affected?
CCCA is diagnosed most frequently in adult Black women, particularly women of African ancestry. Prevalence estimates vary because studies use different populations, ages, examination methods, and definitions of clinically significant central loss. Older research has reported rates in the low single digits in some populations, with prevalence rising with age.
That demographic pattern is important. It should not be misread as a biological accusation against textured hair or Black hairstyling.
Men can develop CCCA. A 2023 male case series documented clinical and histologic disease in men, though CCCA remains reported far more often in women. Children and adolescents can also be affected, but pediatric literature is limited and diagnosis deserves particular care because infection, genetic conditions, traction, alopecia areata, and other inflammatory disorders may resemble it.
People outside the most commonly affected ancestry can develop CCCA too.
Diagnosis may arrive late. A 2026 analysis found that CCCA was associated with a longer time to diagnosis than other scarring alopecias, which is worrying because delay allows more opportunity for irreversible follicular loss.
Why the delay? Early breakage is easy to blame on dryness. The crown is hard to inspect. Symptoms may be absent. And some clinicians have limited training in textured hair, darker scalp findings, or CCCA’s less typical forms. Healthcare access matters as well.
Does “Scarring” Mean Treatment Is Pointless?
No.
Treatment cannot recreate a follicle that has been completely replaced by scar tissue. It may, however, reduce active inflammation, limit further damage, relieve scalp symptoms, and preserve follicles that remain capable of producing hair. Some of those follicles may produce thicker or longer strands once disease activity settles.
Other changes may be reversible too. A short crown hair may be breaking because the shaft is fragile. Another may be miniaturized because female pattern hair loss is present alongside CCCA. Those situations are biologically different from complete follicular destruction.
That is why “Will it grow back?” rarely deserves a one-word answer.
The more useful question is: Which follicles are still there?
A dermatologist estimates that from the visible pattern, retained openings, trichoscopic signs, disease duration, treatment response, and sometimes biopsy findings. Early disease generally leaves more room for recovery than a longstanding smooth patch with extensive follicular dropout.
What Does CCCA Hair Loss Look and Feel Like in Its Early Stages?
Early CCCA may cause localized crown breakage, gradually reduced density, itching, burning, tingling, soreness, scale, or small follicular bumps. Some people have no discomfort. Before obvious scarring develops, it can resemble ordinary breakage or female pattern hair loss.
What Are the Earliest Warning Signs?
One of the earliest clues may be hair breakage at the crown. The strands look shorter than surrounding hair, fail to retain length, or seem to thin in one stubborn area. A case series specifically identified crown breakage as a presenting sign of early or occult CCCA.
Other possible signs include:
- Gradual loss of fullness near the crown
- A widening central area or part
- Short hairs of uneven length
- Persistent itching
- Burning or stinging
- Tingling
- Scalp tenderness
- Pain when moving the hair
- Scale around follicles
- Small bumps or roughness
- A sensation of tightness
Some people notice symptoms before visible thinning. Some notice hair loss first. Others never feel anything unusual.
Silence is not proof of inactivity.
CCCA usually causes progressive thinning and follicular loss rather than sudden handfuls of shedding. When hair is coming out diffusely from across the scalp, another process such as telogen effluvium, thyroid dysfunction, medication effects, postpartum shedding, rapid weight loss, nutritional restriction, or illness may be contributing.
And the conditions can overlap. A person may have CCCA at the crown and telogen effluvium everywhere else. The shower drain will not kindly separate the two into labelled piles.
A localized change deserves attention when it persists, expands, or comes with scalp symptoms. Waiting for a visibly bare patch misses the point of early care.
Does CCCA Always Begin as a Round Patch at the Crown?
The classic pattern begins around the vertex and gradually spreads outward. Early on, the center may look less dense. Later, the involved area may widen, become irregular, or contain scattered surviving hairs.
But no, CCCA does not always form one perfect circle.
The 2024 clinical-presentation review documented several patterns outside the textbook central form, including patchy and more peripheral involvement. A separate 2026 report also described patchy presentation, adding to the warning that clinicians should not reject CCCA merely because the distribution looks unusual.
Early disease may retain normal-looking follicular openings. That makes it easier to confuse with nonscarring thinning. With further destruction, openings become sparse, the scalp may look smooth, and a white or gray halo may appear around affected follicles under magnification.
Shiny scalp raises concern for scarring, but shininess alone is not diagnostic. Lighting, oil, tightly stretched skin, and advanced nonscarring loss can alter appearance too.
CCCA is named after its classic pattern, not a rule every scalp must obey.
How Is CCCA Different From Other Common Causes of Crown Thinning?
Several hair-loss conditions can occupy similar territory. The differences are often subtle enough that guessing from a social-media photograph is unreliable.
|
Condition |
Common pattern |
Scalp symptoms |
Follicular openings |
Useful clue |
|
CCCA |
Often begins around the crown, though atypical forms occur |
Itching, burning, pain, tenderness, scale, bumps, or none |
May become reduced or absent |
Crown breakage with inflammatory or scarring signs |
|
Female pattern hair loss |
Widening part or diffuse central thinning |
Usually few inflammatory symptoms |
Generally retained |
Progressive miniaturization rather than follicular destruction |
|
Traction alopecia |
Hairline, temples, or areas under repeated tension |
Tenderness, bumps, or soreness may occur |
Retained early, potentially lost after longstanding traction |
A clear relationship with pulling styles |
|
Telogen effluvium |
Diffuse shedding across the scalp |
Usually little scalp inflammation |
Retained |
A trigger often occurred two or three months earlier |
|
Alopecia areata |
Smooth focal patches or broader loss |
Often asymptomatic |
Retained |
Sudden patches with characteristic broken or tapering hairs |
|
Lichen planopilaris |
Variable scarring patches |
Itching, pain, scale, perifollicular redness |
Reduced in scarred areas |
Clinical and biopsy overlap with CCCA can be substantial |
|
Discoid lupus erythematosus |
Inflammatory scarring plaques |
Scale, tenderness, pigment change |
May be lost |
Atrophy, follicular plugging, dyspigmentation, and characteristic biopsy findings |
|
Tinea capitis |
Patchy loss with scale and broken hairs |
Itching or tenderness may occur |
Usually retained early |
Fungal testing may be needed, particularly in children |
Female pattern hair loss is nonscarring. Follicles miniaturize, producing progressively finer hairs, but the basic follicular structure remains. CCCA destroys the follicle itself. The two can occur together, which can make the crown look more diffusely thin than either condition would alone.
Traction alopecia usually follows the geography of pulling. Edges and temples are common, though any repeatedly loaded area can be affected. Early traction may improve after tension stops. Longstanding traction can become scarring and permanent.
CCCA and traction can coexist too. That is not a technical footnote. It changes the plan. Medication may be needed for CCCA, while tension reduction addresses the traction component.
Alopecia areata can create strikingly smooth patches, but it does not ordinarily eliminate follicular openings. Tinea capitis may cause broken hairs and scale. Lichen planopilaris and discoid lupus can be harder to separate because they are also primary scarring alopecias.
The scalp examination earns its keep here.
Which Signs Call for Faster Medical Assessment?
Arrange prompt medical care when crown thinning is accompanied by:
- Increasing pain or tenderness
- Burning or severe itching
- Rapid expansion
- Smooth areas with fewer openings
- Significant scale or crusting
- Recurrent follicular bumps
- Progression despite treatment
- Scarring loss in a child
- Eyebrow, eyelash, facial, or body-hair loss
Seek faster evaluation for pus, drainage, marked swelling, fever, painful nodules, boggy scalp, enlarged lymph nodes, or rapid widespread loss. Those findings may point toward infection or another inflammatory disorder rather than uncomplicated CCCA.
A dermatologist with an interest in hair disorders is especially useful when the pattern is unusual, the biopsy is unclear, or treatment is not slowing progression.
A stubborn crown patch deserves a name before it receives another bottle.
What Causes CCCA, and What Has Not Been Proven to Cause It?
No single cause of CCCA has been confirmed. Current evidence points toward a combination of genetic susceptibility, altered follicular biology, inflammation, and fibrosis. Styling-related tension or irritation may add damage in some people, but one hairstyle, product, or chemical practice does not explain every case.
Is CCCA Genetic?
There is credible evidence for genetic susceptibility.
In a landmark 2019 study, researchers identified variants in PADI3, a gene involved in normal hair-shaft formation, among a subset of patients with CCCA. The variants were found in 5 of 16 people in the initial group and additional participants in a 42-person replication group. That supports a genetic contribution. It does not support the idea that every case has one identifiable mutation.
Familial cases have also been described, with inheritance patterns compatible with autosomal dominant transmission in some families. Expression can vary, which means one relative may have mild thinning while another develops extensive disease.
Several limits belong beside those findings:
- A PADI3 variant does not guarantee that CCCA will develop.
- Many people with CCCA do not have an identified PADI3 variant.
- No known variant currently predicts the exact age of onset, severity, or treatment response.
- Routine commercial genetic testing is not required to diagnose CCCA.
- A genetic result does not currently determine the standard medication plan.
Family history is still worth asking about. A mother, sister, aunt, grandmother, or other relative may have called it “thin crown,” “breakage,” or “hair that stopped growing” rather than CCCA.
Genes may load the dice. They do not decide every roll.
Do Braids, Weaves, Relaxers, or Heat Cause CCCA?
A direct, universal causal relationship has not been proved.
The older label hot-comb alopecia reflected a period when central scarring hair loss was largely attributed to grooming practices. Later research made that explanation increasingly difficult to defend. CCCA occurs in women who have never used hot combs or relaxers, while most people who use these methods never develop CCCA.
A retrospective study compared grooming practices in 51 women with CCCA and 50 controls. It found associations with sewn-in weaves and cornrows or braids worn with artificial extensions, particularly when women recalled painful pulling or tenderness. The study did not find a significant relationship with hot-comb use or chemical relaxers.
That study matters. Its limitations matter too.
Participants had to remember past practices. Styling may have changed after hair loss began. The research came from one geographic population. Traction alopecia could have coexisted with CCCA. And an association cannot prove that the style initiated the scarring disease.
What can be said with greater confidence?
Repeated tension can cause traction alopecia. Heavy added hair, painfully tight braids, firm wig attachments, clips, adhesive, and styles that pull for weeks can damage follicles. Chemical burns and direct heat can irritate the scalp or weaken hair shafts. Those injuries may complicate CCCA, worsen breakage, or add a second form of hair loss.
Reducing extra injury is sensible. Assigning blame is not.
This distinction is more than polite wording. Black women have repeatedly been handed medical advice that amounts to “stop doing your hair that way,” with little recognition of culture, cost, work expectations, maintenance time, stylist access, personal preference, or the maddening practical question of what to do instead.
A useful plan asks whether a style hurts, pulls, burns, adds substantial weight, blocks medication, or makes examination difficult. It does not place every braid, twist, wig, loc, or relaxer into one moral bucket.
What Inflammatory and Fibrotic Processes May Be Involved?
CCCA is generally classified as a lymphocytic primary scarring alopecia because lymphocytes are often seen around affected follicles. Over time, inflammatory injury can be followed by fibrosis and loss of normal follicular structures.
Molecular research has identified increased expression of genes involved in fibrosis, extracellular matrix formation, and abnormal tissue repair in CCCA scalp. One study found preferential expression of fibroproliferative genes, helping support the view that fibrosis is not merely a passive leftover at the end of inflammation.
More recent transcriptomic work continues to implicate inflammatory and fibrotic pathways across primary lymphocytic scarring alopecias. Still, molecular overlap does not prove that every case begins through the same trigger.
CCCA is inflammatory. Whether it should be called a uniform autoimmune disease remains less certain.
A June 2026 multi-institutional cross-sectional study examined autoimmune disease in people with CCCA, adding fresh observational evidence to the discussion. Cross-sectional association cannot prove that one condition causes the other, and it does not turn every case into a conventional autoimmune disorder overnight.
For now, “immune involvement may contribute” is fair. “CCCA is definitively autoimmune” is too tidy.
What Has Not Been Shown to Be the Primary Cause?
Current evidence does not establish any of the following as the sole primary cause of CCCA:
- Poor scalp circulation
- Reduced blood flow
- Product buildup
- Clogged follicles
- Excess sebum
- DHT alone
- Estrogen loss alone
- Emotional stress alone
- Iron deficiency
- Vitamin D deficiency
- Seborrheic dermatitis
- Bacterial infection
- Fungal infection
Some deserve nuance.
Iron deficiency, thyroid dysfunction, rapid weight loss, and severe stress can cause additional shedding. Seborrheic dermatitis may add itching and scale. Tinea capitis may mimic patchy loss. Hormonal pattern hair loss can occur beside CCCA. A scalp microbiome pilot study has also examined whether bacterial and fungal communities differ in CCCA, but early microbiome findings do not establish infection as the cause or justify antimicrobial treatment for everyone.
Coexistence is not causation.
That phrase will come up again because CCCA research contains many associations that are interesting, biologically plausible, and nowhere near ready for a sweeping headline.
Is CCCA Linked With Diabetes, Fibroids, Autoimmune Disease, or Cancer?
Several health associations have been reported. The findings are mixed.
Earlier observational work suggested that type 2 diabetes might be more common in people with CCCA. A later large multicenter database study found no meaningful increase in type 2 diabetes, prediabetes, obesity, or metabolic syndrome when CCCA patients were compared with people who had other scarring alopecias.
A separate 2026 case-control study reported no association between CCCA and type 2 diabetes or hypertension.
This does not mean metabolic health is irrelevant. It means CCCA alone should not be used to announce that someone has insulin resistance or needs a special metabolic workup outside ordinary clinical risk assessment.
An association between CCCA and uterine fibroids was reported in a 2018 cohort study. Later molecular work found that the presence of fibroids did not significantly alter the scalp gene-expression profile of patients with CCCA.
CCCA does not prove fibroids. Fibroids do not prove CCCA.
A small retrospective pilot study also reported a higher recorded prevalence of breast cancer among women with biopsy-confirmed CCCA. The authors noted major limitations, including selection bias, healthcare-use differences, incomplete control of breast-cancer risk factors, and the possibility that cancer treatment itself affected hair.
That study does not show that CCCA causes breast cancer. It is not sufficient reason to order extra cancer screening beyond established age, family-history, symptom, genetic, and clinician-based recommendations.
Readers with heavy menstrual bleeding, pelvic pressure, persistent fatigue, breast changes, or other concerning symptoms should seek appropriate medical care because of those symptoms, not because a hair article has frightened them into a testing spree.
How Do Dermatologists Diagnose CCCA?
A dermatologist usually diagnoses CCCA by combining the medical history, scalp examination, trichoscopy, and sometimes a scalp biopsy. Blood tests cannot confirm CCCA, though targeted testing may identify another cause of shedding or a condition occurring alongside it.
What Happens During the Scalp Examination?
The appointment starts with questions that may feel surprisingly detailed.
A dermatologist may ask:
- When did thinning or breakage begin?
- Did pain, burning, itching, scale, or bumps come first?
- Has the affected area expanded?
- Is shedding localized or diffuse?
- Does anyone in the family have crown thinning?
- Which styles, chemicals, heat methods, or attachments have been used?
- Did any style hurt during installation?
- Has there been illness, surgery, childbirth, rapid weight change, or nutritional restriction?
- Which medications and supplements are being taken?
- Is pregnancy, breastfeeding, or conception relevant to treatment planning?
Then comes the scalp examination. The clinician should inspect the crown, part lines, hairline, temples, sides, and back of the scalp rather than staring only at the most obvious patch.
They may look for:
- Broken hairs
- Hair-caliber variation
- Scale
- Perifollicular redness
- Pigment changes
- Bumps or pustules
- Tenderness
- Smooth areas
- Visible follicular openings
- Signs of traction
- Features suggesting another scarring alopecia
Redness on deeply pigmented skin may appear brown, gray, violaceous, or subtler than the bright-red examples in many medical textbooks. Familiarity with skin of color matters.
Trichoscopy, also called scalp dermoscopy, provides magnified views of the follicles, hair shafts, openings, pigment patterns, and surrounding skin. Reported CCCA findings include a peripilar white or gray halo, irregular white patches, reduced follicular openings, scale, and other signs that vary with stage.
Trichoscopy can also help identify a biopsy site. Sampling the wrong spot, particularly a shiny center where little active tissue remains, may produce an unhelpfully vague pathology report.
It is a useful tool. Not an oracle.
When Is a Scalp Biopsy Needed?
Not every patient requires a biopsy.
A dermatologist may recommend one when:
- The pattern is early or atypical
- CCCA and female pattern hair loss are difficult to separate
- Several scarring alopecias remain possible
- The visible findings are subtle
- Treatment intensity depends on diagnostic certainty
- Hair loss continues despite treatment
- A costly procedure such as transplantation is being considered
The clinician numbs the selected area and removes a small cylindrical sample, commonly with a punch instrument. Depending on the diagnostic question and local pathology method, one or two samples may be taken so the tissue can be examined in horizontal and vertical sections.
The sample should usually come from an active edge containing follicles, not the bare center of an old scar. That allows the pathologist to assess inflammation, fibrosis, sebaceous glands, follicular architecture, and inner-root-sheath changes.
Possible findings include:
- Perifollicular lymphocytic inflammation
- Concentric fibrosis
- Premature inner-root-sheath desquamation
- Loss of sebaceous glands
- Follicular dropout
- Fibrous tracts
A biopsy can help distinguish CCCA from lichen planopilaris, discoid lupus, longstanding traction alopecia, and other causes. Even then, overlap occurs. A comparative study found substantial histopathologic similarities between CCCA and lichen planopilaris, reinforcing the need to interpret tissue beside the clinical pattern.
Local anesthetic reduces pain during the procedure. The site may feel tender afterward and leaves a small permanent scar. Hair does not regrow from the tiny piece of skin that was removed.
Late-stage biopsies can be nonspecific because active inflammation may have faded, leaving mostly scar tissue. A nondiagnostic biopsy does not mean the symptoms were invented. Sometimes the site, disease stage, sectioning method, or overlapping conditions simply make the answer harder to obtain.
Which Blood Tests Might Be Useful?
No blood test diagnoses CCCA.
Laboratory testing is used to investigate another contributor to hair loss or a separate health concern.
Depending on the history, a clinician may consider:
- Complete blood count
- Ferritin and iron studies
- Thyroid testing
- Vitamin D or other nutrient testing when deficiency risk exists
- Glucose or A1C based on standard medical risk
- Autoimmune testing when symptoms suggest lupus or another systemic disorder
- Fungal testing when tinea capitis is possible
Broad testing without a clinical reason can create noise. A mildly abnormal result may be incidental. A normal result does not rule CCCA out. And treating an unrelated laboratory value will not repair a follicle already replaced by fibrosis.
Iron should not be taken blindly. High supplemental doses can cause nausea, constipation, interactions, and toxicity. (National Institutes of Health Office of Dietary Supplements [NIH ODS], 2025)
Biotin does not treat CCCA. Evidence supporting routine high-dose biotin for hair growth in people without deficiency is weak, and excessive biotin can interfere with thyroid, hormone, vitamin D, cardiac, and other laboratory assays.
Tell the clinician about every supplement. The neon bottle with “hair” in giant letters still counts as a supplement, even if the label has leaves on it and behaves very confident.
How Should You Prepare for the Appointment?
A little preparation can make the visit much more productive.
Bring or record:
- When the change first appeared
- Whether breakage, thinning, shedding, or symptoms came first
- Photographs from before and during progression
- Family history of central thinning or scarring alopecia
- Medications and supplements
- Hair-care practices
- Any painful style, chemical burn, or scalp reaction
- Pregnancy, breastfeeding, or conception plans
- Previous laboratory or biopsy reports
Remove or loosen any style that blocks access to the affected scalp. The dermatologist needs to examine skin, openings, scale, and individual hairs. A beautifully installed style that hides the entire crown is medically inconvenient, even if it deserves applause on every other level.
Questions worth asking include:
- What diagnosis is most likely?
- What findings support it?
- Does the scalp look actively inflamed, scarred, or both?
- Could another form of hair loss be present?
- Is trichoscopy enough, or would biopsy help?
- Which treatment controls inflammation?
- Which treatment only supports density?
- How will progress be measured?
- What adverse effects require a call?
- Does the clinic have a financial interest in the recommended product or procedure?
That final question is not rude. It is part of informed consent.
How Is CCCA Treated, and How Much Regrowth Is Realistic?
CCCA hair loss treatment focuses first on reducing inflammation and protecting follicles from further damage. Corticosteroids are commonly used, sometimes with another anti-inflammatory medicine. Minoxidil may support viable follicles or coexisting pattern hair loss. Fully scarred follicles generally cannot regrow.
What Is Treatment Actually Trying to Achieve?
A sound treatment plan has four separate aims:
- Reduce active inflammation
- Relieve itching, burning, pain, or tenderness
- Slow or stabilize further follicular destruction
- Support growth from follicles that remain viable
There is no universally established CCCA treatment protocol. In a 2024 modified Delphi study, 27 US hair specialists were invited to rate treatment statements over three rounds. Strong consensus was reached for only 20 of 70 statements.
That is not an argument against treatment. It is a reminder that much of current practice rests on specialist agreement, retrospective evidence, small studies, and clinical judgment rather than large randomized comparisons.
Treatment is individualized according to:
- Symptoms
- Rate of progression
- Visible inflammation
- Extent of fibrosis
- Biopsy findings
- Coexisting pattern hair loss
- Age
- Pregnancy plans
- Medical history
- Medication tolerance
- Cost and access
Stabilization may mean the area stops expanding, symptoms improve, trichoscopic inflammation settles, breakage decreases, and existing density is preserved.
Preservation can look unimpressive in a before-and-after advertisement. Clinically, it may be the win.
Why Are Topical and Injected Corticosteroids Commonly Used?
Corticosteroids suppress inflammation, which is why topical preparations and intralesional injections are common starting points for active CCCA.
A dermatologist may prescribe a potent topical corticosteroid for regular use during an initial period, then reduce the frequency as symptoms and visible activity settle. Another option is intralesional corticosteroid, often triamcinolone, injected into or around active areas.
These medicines do not directly rebuild scarred follicles. Their job is to reduce the inflammatory attack and protect what remains.
Potential adverse effects of topical or injected corticosteroids include:
- Skin thinning
- Folliculitis
- Acne-like bumps
- Pigment changes
- Small visible blood vessels
- Local tenderness
- Temporary or persistent indentation after injections
Risk depends on the medicine, potency, concentration, amount, injection depth, frequency, surface area, and duration.
This is why copying somebody else’s “CCCA routine” from a comment section is unwise. One person’s scalp, steroid strength, injection concentration, and disease stage may bear very little resemblance to another’s.
Systemic corticosteroids may occasionally be considered for unusually rapid or severe inflammatory activity. Their broader risks make them a specialist decision rather than a casual long-term solution.
Why Might a Dermatologist Prescribe Doxycycline, Minocycline, or Tacrolimus?
Doxycycline and minocycline are antibiotics, but in CCCA they may be used mainly for anti-inflammatory effects. Their prescription does not mean the condition is ordinarily caused by bacteria.
A 2024 single-center retrospective analysis examined doxycycline use in CCCA, adding condition-specific clinical data to a practice that had previously rested heavily on expert use and extrapolation. Retrospective findings remain less certain than randomized evidence.
Treatment may continue for several months because inflammatory scalp disease does not necessarily settle on a convenient two-week calendar.
Doxycycline can cause:
- Nausea
- Abdominal discomfort
- Esophageal irritation
- Diarrhea
- Sun sensitivity
- Drug and supplement interactions
Official prescribing information also includes pregnancy, tooth-development, bone-growth, allergy, and serious-diarrhea warnings.
Minocycline has a different adverse-effect profile and may cause dizziness, pigment changes, hypersensitivity reactions, or autoimmune-like complications in rare cases.
Topical calcineurin inhibitors, such as tacrolimus or pimecrolimus, may be used as steroid-sparing anti-inflammatory options. Temporary burning or stinging can occur.
Hydroxychloroquine and stronger systemic immunomodulatory medicines are sometimes considered for persistent or difficult inflammatory disease. Direct CCCA evidence is limited. Hydroxychloroquine requires appropriate retinal-risk assessment and eye monitoring because cumulative exposure can damage the retina.
Medication selection must account for pregnancy, breastfeeding, fertility plans, liver and kidney health, blood counts, infections, interactions, and other medical conditions.
Does Minoxidil Treat CCCA?
Minoxidil may support growth from viable follicles. It does not adequately control active CCCA inflammation on its own.
The AAD specifically cautions that minoxidil alone cannot prevent CCCA-related hair loss from progressing. Prescription treatment is generally needed to address inflammation.
Topical minoxidil may be especially useful when:
- Some affected follicles remain viable
- Hair shafts have miniaturized
- Female pattern hair loss coexists
- Inflammation is being treated separately
- The clinician wants to support density during stabilization
Potential effects include initial temporary shedding, scalp irritation, dryness, contact dermatitis, and unwanted facial hair if the medicine spreads beyond the scalp. Visible change takes months, and benefit often requires continued use.
Low-dose oral minoxidil is prescribed off-label by some dermatologists. A 2024 review of topical and oral minoxidil in scarring alopecias found possible benefit, while emphasizing variable outcomes, limited evidence, and the need for further study.
Oral minoxidil can cause:
- Increased facial or body hair
- Ankle swelling
- Fluid retention
- Palpitations
- Faster heart rate
- Blood-pressure changes
- Headache or light-headedness
It requires medical assessment.
The cleanest way to separate the jobs is this:
Disease control: prescription anti-inflammatory treatment
Density support: minoxidil and selected adjuncts
Neither topical nor oral minoxidil can recreate a fully scarred follicle.
What Newer or Experimental Treatments Are Being Studied?
CCCA research has gained momentum. That is encouraging. It has not suddenly produced a shelf full of proven cures.
|
Treatment |
What has been reported |
Current evidence limit |
|
Topical metformin |
Case reports describing improvement or regrowth |
No controlled CCCA trial |
|
Low-dose oral metformin |
A 12-patient retrospective series in treatment-resistant CCCA |
No placebo group, concurrent treatments, single specialist center |
|
Apremilast |
Small open-label pilot study |
Uncontrolled, underpowered, short follow-up |
|
JAK or TYK2 pathway medicines |
Case-level or mixed-scarring-alopecia reports |
Very little CCCA-specific evidence |
|
Platelet-rich plasma |
Sparse case-level literature, with a placebo-controlled trial registered |
No established preparation or standard protocol |
|
Microneedling |
Little direct CCCA evidence |
Uncertain safety and value in active scarring disease |
|
Exosome or stem-cell procedures |
Commercial availability in some settings |
No robust CCCA efficacy evidence |
Metformin
A 2020 paper described two patients with treatment-resistant CCCA who had regrowth after topical metformin. Two patients can justify further study. They cannot establish average benefit, ideal concentration, long-term safety, or superiority to standard care. (Araoye et al., 2020)
A separate 2025 case report and literature review described topical metformin 10% cream. It remains case-level evidence. (Granja et al., 2025)
A 2024 retrospective series studied low-dose oral metformin in 12 Black women with biopsy-confirmed, treatment-resistant CCCA. Nine had symptomatic or clinical improvement, six showed clinical regrowth after at least six months, and paired gene-expression analysis was available for only four participants. Everyone remained on baseline treatment. There was no randomized control group. (Bao et al., 2024)
Useful signal? Yes.
Established therapy? Not yet.
Apremilast
A 2025 open-label pilot enrolled 20 women, with 15 completing 24 weeks. Some physician and patient outcomes improved, while several secondary measures did not reach statistical significance. The study was small, uncontrolled, and affected by pandemic disruption. (Cices et al., 2025)
Apremilast remains investigational for CCCA.
JAK and Other Targeted Immune Medicines
Biologics and JAK inhibitors are being reported across several scarring alopecias. A 2025 review found signals worth studying, particularly for selected immune pathways, but the evidence was largely off-label and heterogeneous. (Agarwal et al., 2025)
Results from lichen planopilaris, frontal fibrosing alopecia, or alopecia areata cannot be assigned automatically to CCCA. These medicines may carry serious infection, clotting, cardiovascular, malignancy, laboratory, and reproductive considerations.
Platelet-Rich Plasma
Platelet-rich plasma, or PRP, involves concentrating platelets from the patient’s blood and injecting the preparation into the scalp. CCCA evidence remains sparse, and protocols vary in platelet concentration, activation, injection depth, volume, and treatment schedule.
A placebo-controlled CCCA PRP trial is registered on ClinicalTrials.gov. Registration means the question is being tested. It does not supply a positive result before the study reports one. (ClinicalTrials.gov, 2025)
A 2025 systematic review of procedures for scarring alopecia concluded that procedural options may help selected patients with symptoms or limited regrowth, but should remain adjunctive while standardized controlled evidence is lacking. (Tanha et al., 2025)
Microneedling, Exosomes, and Stem-Cell Procedures
Microneedling deliberately creates small skin injuries. That may be acceptable in certain nonscarring conditions under appropriate care, but active inflammatory scarring alopecia is a different biological situation. CCCA-specific efficacy and safety data are insufficient.
Commercial exosome and stem-cell injections present additional concerns around product content, manufacturing consistency, sterility, regulation, dosing, and long-term outcomes.
Expensive does not mean established.
Anecdotal does not mean useless either, but it belongs in the correct evidence drawer.
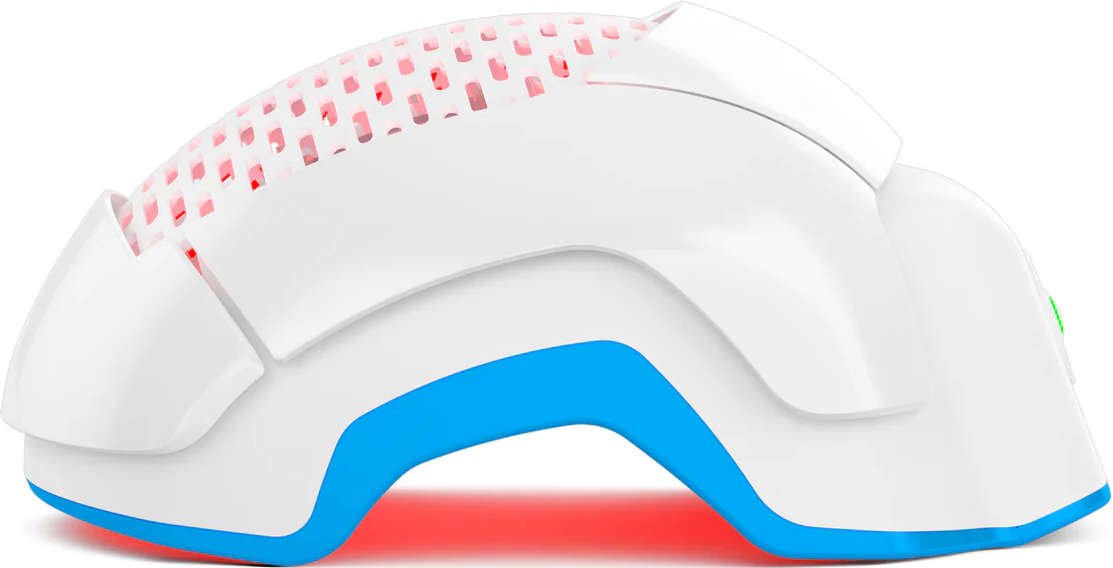
Can Laser Phototherapy or Theradome Treat CCCA?
Light-based therapy for CCCA remains preliminary.
A 2023 publication reported outcomes in four patients who received low-level light treatment. Four people cannot establish average effectiveness, identify who benefits, or determine whether improvement came from light treatment rather than concurrent care. (Cook et al., 2023)
A later uncontrolled interventional cohort assessed a specific dual-wavelength light device in women receiving CCCA care. The brief report was published in 2026. It suggested possible improvements in selected symptoms and hair measures, but the small cohort, lack of a placebo group, device-specific protocol, and concurrent treatment limit what can be concluded. (Larrondo et al., 2026)
Several boundaries are essential:
- Evidence from an LED device does not automatically establish the performance of a laser device.
- Results from one device cannot be assumed for every red-light product.
- Improvement in hair density does not prove reversal of scar tissue.
- Light treatment should not replace medication intended to control active inflammation.
- Clearance for androgenetic alopecia does not establish a CCCA indication.
Theradome is FDA-cleared for androgenetic alopecia, within the male and female pattern classifications stated in its clearance documents.
If a person has both CCCA and androgenetic alopecia, a dermatologist may consider separate treatment for each diagnosis. Laser phototherapy might be discussed for the androgenetic component. That is different from claiming it treats follicular scarring.
For active CCCA, light treatment should not replace prescription care aimed at controlling inflammation.
Can Hair Transplantation or Cosmetic Camouflage Help?
Hair transplantation may be considered in carefully selected patients whose disease has remained clinically inactive.
The difficulty is proving inactivity.
Symptoms may disappear while low-level inflammation persists. A clinician may use serial photographs, trichoscopy, examination, and sometimes biopsy before discussing surgery. There is no universally validated waiting period, though published practice often calls for prolonged stability.
A 2025 systematic review of follicular-unit graft survival in primary cicatricial alopecia found limited and heterogeneous evidence. Graft survival can be lower in scarred tissue, follow-up is often short, and disease reactivation remains a concern. (Yii et al., 2025)
A small test transplant may be considered before a larger procedure. The donor area also needs evaluation because CCCA can occasionally involve areas beyond the central scalp.
Nonsurgical options include:
- Wigs
- Toppers
- Hair fibers
- Scalp concealers
- Strategic styling
- Scalp micropigmentation in selected stable cases
Wig combs, clips, tight caps, heavy hairpieces, and adhesive can create tension or irritation. Camouflage should make daily life easier, not quietly add another injury pattern.
How Long Does Treatment Take, and How Is Progress Measured?
Scalp symptoms may improve before hair density changes. Hair growth is slow, and visible improvement usually takes months.
A dermatologist may monitor:
- Itching, burning, tenderness, and pain
- Perifollicular scale or redness
- New breakage
- Expansion of the affected area
- Trichoscopic signs
- Hair caliber and length
- Standardized photographs
- Treatment adherence
- Adverse effects
The Central Scalp Alopecia Photographic Scale has historically been used to document central loss. A newer C-CAT scoring tool was introduced in 2025 to provide a broader structured method for tracking CCCA severity and response, though some components remain subjective and may vary between raters. (Qadri et al., 2025)
Progress photographs work best when the lighting, part, angle, camera distance, hairstyle, and hair condition remain similar. Otherwise, one photo may look thicker simply because the hair is fluffed, longer, freshly washed, darker, or standing three inches closer to the lens.
Six to twelve months may be needed to judge density change fairly. Rapid progression deserves reassessment sooner.
Treatment may be tapered after stabilization. Some patients require maintenance therapy. Recurrence can happen.
And sometimes the most meaningful result is quiet: the patch did not get larger.
What Can You Do Now to Protect Your Scalp and Remaining Hair?
Gentle hair care can reduce added traction, irritation, and breakage. It cannot replace medical treatment for active CCCA. The goal is not to outlaw every preferred hairstyle. It is to remove practices that hurt, pull, burn, abrade, or prevent proper scalp care.
Which Styling Changes Are Reasonable?
A hairstyle should not hurt during installation or remain painful afterward.
Reasonable adjustments include:
- Loosening braids and twists
- Reducing the weight of added hair
- Avoiding repeated tension over the same crown area
- Repositioning wig clips or combs
- Using less restrictive wig caps
- Stopping styles that cause bumps, burning, headaches, or persistent soreness
- Keeping relaxer and dye away from inflamed or broken skin
- Reducing direct high heat on tender scalp
- Allowing the scalp to remain accessible for medication and examination
A protective style is not automatically gentle. A natural hairstyle is not automatically protective. The useful questions are mechanical.
Does it hurt?
Does it pull?
Is it heavy?
Does the scalp stay sore?
A person may decide to pause chemical relaxing while inflammation is active, especially if application causes burning or irritation. That does not mean relaxers have been proved to cause CCCA, nor that stopping them guarantees stabilization.
Ask the stylist to mention expanding crown breakage, tenderness, scale, or a visible change in density. Stylists often see the crown more clearly and more regularly than the person sitting beneath it.
They cannot diagnose CCCA. They can notice that something is changing and recommend medical assessment.
How Should You Wash and Care for the Scalp?
There is no universal CCCA wash schedule.
Frequency should account for:
- Hair texture
- Scalp oil and sweat
- Scale
- Medication vehicle
- Hairstyle
- Exercise
- Tenderness
- Coexisting seborrheic dermatitis
The scalp needs to be clean enough for prescribed medication to reach the skin. Shampooing does not cause follicular scarring when performed gently.
Avoid aggressive scratching, scraping, fingernail digging, or stiff scalp brushes on painful areas. Those methods may feel satisfying for fourteen seconds and leave the scalp substantially angrier afterward.
A medicated dandruff shampoo may help a coexisting scaling condition. It does not treat CCCA fibrosis.
Conditioner can reduce friction and make detangling easier. Work carefully through the ends before moving upward. For a fuller distinction between snapped strands and root-level loss, see Theradome’s guides to hair breakage and hair breakage at the crown.
Oils may lubricate hair shafts or reduce dryness. They do not reopen scarred follicles.
Vigorous massage has not been shown to break up fibrosis. CCCA is not a knot in the scalp waiting to be kneaded loose.
Do Food, Supplements, or Home Remedies Help?
No diet has been shown to cure CCCA.
Adequate calories, protein, iron, and other nutrients support general hair production. Correcting a documented deficiency may improve a separate shedding problem. It does not reverse established follicular scarring.
Avoid restrictive plans that eliminate broad food groups without a sound medical reason. Severe restriction can create additional shedding, which is an especially unfair reward for all that culinary misery.
Routine biotin is not a CCCA treatment. (NIH ODS, 2022)
There is no adequate evidence that any of the following reverses CCCA scarring:
- Castor oil
- Rosemary oil
- Collagen
- Saw palmetto
- Turmeric
- Rice water
- Onion juice
- Garlic
- Cayenne pepper
- “Detox” supplements
- Scalp-cleansing powders
Some oils can improve lubrication and reduce hair-shaft friction. That may help hair feel softer or retain length. It is not the same biological outcome as restoring a destroyed follicle.
Essential oils, acids, peppers, garlic, and concentrated botanical mixtures may cause irritant or allergic dermatitis. An inflamed scalp does not need seven kitchen ingredients holding a committee meeting on it.
What About the Emotional Toll?
CCCA can affect far more than density.
People may feel grief, embarrassment, anger, salon anxiety, concealment fatigue, fear of dating, discomfort in photographs, or dread when wind and water interfere with carefully arranged coverage. Healthcare costs, repeated appointments, prescription expenses, wigs, and procedures add another layer.
A survey of women with CCCA found barriers related to physician knowledge of Black hair and reported effects on self-esteem and quality of life. (Akintilo et al., 2019)
None of that is vain.
Hair carries cultural, personal, familial, and social meaning. Losing it can feel like losing privacy too, because the condition becomes visible before a person has decided whether to discuss it.
Helpful support may include:
- A dermatologist who takes symptoms seriously
- A stylist willing to work within the medical plan
- A therapist or counsellor
- A scarring-alopecia support group
- Practical wigs, toppers, fibers, or scalp concealers
- Honest conversation with trusted family or friends
The medical goal is to protect follicles. The human goal is broader. It includes helping someone feel like herself while the clinical work proceeds.
What Can You Do While Waiting for the Appointment?
- Take clear photographs under consistent lighting.
- Note when symptoms and thinning began.
- Stop styles that cause pain, burning, or strong tension.
- Avoid harsh DIY scalp applications.
- List all medicines and supplements.
- Gather older photographs and family history.
- Keep the scalp accessible for examination.
- Seek faster care if there is pus, fever, rapid spread, marked swelling, or severe pain.
Do not start someone else’s prescription medication. Do not buy an expensive procedure before the diagnosis and disease activity are reasonably clear.
Most of all, do not wait for the area to become dramatically bare before asking.
Conclusion
CCCA can permanently damage hair follicles, but its course is not identical for everyone. Early diagnosis gives a dermatologist a better chance to calm inflammation and protect follicles that remain viable.
Persistent crown breakage, burning, itching, tenderness, smooth scalp, or expanding thinning deserves medical assessment rather than another round of guesswork. Treatment may include topical or injected corticosteroids, additional anti-inflammatory medicines, and density support such as minoxidil where appropriate.
Fully scarred follicles cannot be promised regrowth. Existing hair may still be protected, though, and some viable follicles can improve.
The goal is not perfect certainty at home. It is getting the right scalp examined while there is still hair worth protecting.