Eunuchs can lose hair. What they appeared strongly protected from, especially when testicular androgen production was absent before puberty, was classic male pattern hair loss. That peculiar observation helped reveal a core principle of androgenetic alopecia: sufficient androgen signaling must act on genetically susceptible scalp follicles.
It did not prove that every bald man has high testosterone. It did not explain alopecia areata, telogen effluvium, scarring alopecia, traction, infection, or nutritional shedding. And, rather importantly, it did not make castration a sensible hair-loss treatment.
Ancient medicine got plenty wrong. This one observation, though, kept tapping science on the shoulder for more than two thousand years.
What the Eunuch Clue Proved, and What It Did Not
|
The evidence supports |
The evidence does not support |
|
Classic male pattern loss requires adequate androgen signaling |
Eunuchs are immune to every form of alopecia |
|
Inherited follicular susceptibility affects who develops baldness |
Every bald man has unusually high testosterone |
|
Reducing androgen stimulation can slow or stop further progression |
Removing androgen stimulation reliably restores a long-bald hairline |
|
Age at loss of testicular function matters |
Castration is an acceptable treatment for routine pattern loss |
|
Male androgenetic alopecia is biologically distinct from many other hair disorders |
All hair loss is hormonal |
The historical evidence concerns ordinary androgen-dependent pattern loss. It cannot tell one reader why their hair is shedding, snapping, receding, or disappearing in patches.
Do Eunuchs Really Never Go Bald?
No. A eunuch could still lose hair after severe illness, autoimmune disease, infection, nutritional deficiency, medication exposure, repeated pulling, chemical injury, or a scarring scalp disorder. The useful historical observation was narrower: men who lacked ordinary testicular androgen exposure, particularly before puberty, did not appear to develop the usual adult male pattern of frontal and crown baldness.
Which Kind of Baldness Did the Old Observation Describe?
The ancient writers were probably referring to the conspicuous form of adult male baldness now called male androgenetic alopecia, male pattern hair loss, or male pattern baldness.
In men, this condition usually begins above the temples, at the frontal hairline, through the mid-scalp, at the vertex, or in some combination of those regions. The sides and back are often relatively preserved. Over time, frontal and crown areas may join, leaving a rim of hair around the lower scalp.
Ancient physicians did not have trichoscopy, scalp biopsy, hormone assays, fungal culture, standardized photography, or a formal distinction between scarring and nonscarring alopecia. They saw an outward pattern. A good one, as it happens.
But seeing a pattern is not the same as diagnosing every follicle involved.
The title therefore needs its question mark. “Eunuchs do not develop classic male-pattern baldness under ordinary conditions of profound prepubertal androgen deficiency” would be more precise, though it does struggle slightly as dinner conversation.
What Did “Eunuch” Mean Medically?
Historically, eunuch was not one uniform medical diagnosis.
The term could describe people who had undergone removal or destruction of both testes, partial injury, castration before puberty, castration after puberty, or other genital procedures. It was also a social and political designation whose exact meaning changed by place and period.
An orchiectomy means removal of one or both testes. It does not necessarily mean removal of the penis (a detail the internet occasionally handles with all the delicacy of a dropped saucepan).
Age mattered enormously.
When testicular androgen production was absent before puberty, the usual pubertal development of beard hair, body hair, voice changes, muscle distribution, and androgen-dependent scalp changes was reduced or absent. If castration occurred after puberty, many of those changes had already taken place. A susceptible follicle might already have spent years responding to androgens.
Testicular removal also does not make every androgen molecule vanish. The adrenal glands continue producing weaker androgen precursors, and peripheral tissues can metabolize circulating steroids locally. Profoundly reduced is not always chemically zero.
A historical eunuch is therefore not interchangeable with a modern patient who has mildly low testosterone, pituitary disease, medication-induced hypogonadism, age-related hormonal change, or one remaining testis.
Which Hair-Loss Conditions Could Still Occur?
Many.
Alopecia areata is an autoimmune disorder that can cause smooth patches, diffuse loss, or loss of eyebrows and body hair. It does not require the DHT-sensitive pattern involved in male androgenetic alopecia.
Telogen effluvium can cause diffuse shedding after illness, fever, surgery, childbirth, rapid weight loss, marked nutritional restriction, medication change, or severe physiological strain.
Traction alopecia follows repeated pulling. Tight styles, extensions, adhesives, headwear, or chronic mechanical tension may damage follicles, particularly around the margins.
Tinea capitis is a fungal scalp infection. It can produce scale, broken hairs, inflammation, tenderness, and patchy loss.
Scarring alopecias destroy follicles through inflammatory or fibrotic processes. Once a follicle has been replaced by scar tissue, hormonal protection against male-pattern miniaturization becomes rather beside the point.
Hair can also snap from bleach, relaxers, excessive heat, friction, rough detangling, or shaft disorders. That may resemble reduced density without the follicle itself being lost.
So yes, a eunuch could go bald.
Just not necessarily in the particular way Hippocrates and Aristotle noticed.
What Did Hippocrates and Aristotle Actually Notice?

The earliest surviving statement commonly cited comes from the Hippocratic Aphorisms, not from Aristotle.
Aristotle later described the same association in greater detail and attempted to explain it through ancient ideas about semen, heat, moisture, age, and sexual development. His mechanism was wrong. His observation was annoyingly durable.
What Did the Hippocratic Aphorisms Say?
Book VI, Aphorism 28 of the Hippocratic Aphorisms states:
“Eunuchs neither get gout nor grow bald.”
That wording appears in the Greek medical collection traditionally associated with Hippocrates. (Hippocrates, trans. 1931)
It is safer to say the Hippocratic tradition recorded the observation than to insist that Hippocrates personally wrote that exact sentence. The Hippocratic Corpus includes works composed by more than one author over time, and authorship of individual passages is not always secure.
Still, the line is old. It predates modern endocrinology by a distance that is almost rude.
The aphorism offered no controlled comparison, participant count, hormone measurement, or explanation of what kind of alopecia was being observed. It was compressed clinical pattern recognition. Men without ordinary testicular development apparently did not acquire the characteristic bald crowns and receded hairlines seen in other adult men.
That was the seed.
How Did Aristotle Explain the Same Pattern?
In Book V of Generation of Animals, Aristotle wrote that women and eunuchs did not become bald in the same way as adult men. He also observed that people castrated before maturity did not develop much of the hair that usually appears later in life. (Aristotle, trans. Platt)
His explanation rested on an ancient biological framework involving age, sexual maturity, seminal secretion, bodily heat, and moisture. Aristotle associated baldness with men who produced abundant semen. He believed the frontal scalp was especially vulnerable because of the brain’s location and its supposed heat-and-moisture relationships.
Modern readers may be tempted to laugh.
A little restraint is useful. Aristotle had no testosterone assay, no microscope capable of showing a dermal papilla, no concept of steroid receptors, no molecular genetics, and no enzyme biochemistry. He was trying to account for several observations at once:
- Baldness usually occurred after sexual maturation
- Men developed it more often than women
- Eunuchs rarely showed the same pattern
- Beard and body hair behaved differently from scalp hair
- Frontal scalp hair was commonly affected
The explanatory machinery failed. The observational scaffold did not.
What Did the Ancient Physicians Get Right?
They linked ordinary male baldness with postpubertal sexual biology.
That was no small insight.
The ancient accounts also recognized that the same male developmental state associated with beard and body hair was somehow connected with loss of scalp hair. That contradiction still catches modern readers: why would the hormonal environment that helps a beard thicken make susceptible scalp hairs become finer?
They also noticed timing.
Castration before puberty produced a different hair pattern from castration after sexual maturation. Puberty was the hinge, though nobody yet knew what was swinging on it.
And they noticed geography. Frontal scalp hair behaved differently from hair elsewhere on the body.
All of that pointed toward tissue-specific hormonal response.
What Did They Get Wrong?
They did not know about:
- Testosterone
- DHT
- 5-alpha-reductase
- Androgen receptors
- Dermal papilla cells
- Polygenic susceptibility
- The anagen, catagen, telogen, and exogen phases
- Follicular miniaturization
- Regional gene expression
- Local steroid metabolism
Their explanations relied on heat, moisture, semen, age, and sex differences described through ancient physiology.
The observation was useful. The mechanism was not merely incomplete. It was pointed in the wrong biological direction.
Yet a wrong explanation can sit beside an accurate observation. Medicine has carried more than a few of those combinations through history.
Why Did This Clue Matter for So Long?
Because it was visible.
No blood test was needed to notice that adult men, women, boys, and prepubertally castrated males showed different patterns of facial, body, and scalp hair. The association could be seen repeatedly across generations.
Scientific explanation often arrives long after human observation. The waiting period here was unusually theatrical, but the pattern is familiar. People notice. Someone records it. Centuries later, better tools tell us why.
The eunuch clue endured because it was specific enough to survive the bad theory attached to it.
How Did James Hamilton Turn the Ancient Clue Into Human Evidence?
In 1942, James B. Hamilton published one of the foundational human investigations of male pattern baldness.
Hamilton did not merely note that castrated men kept their hair. He separated participants according to when testicular insufficiency began, examined their scalp patterns, considered family history, and administered testosterone to a selected subgroup. The results supported a two-part model: adequate androgen exposure plus inherited susceptibility.
The research was scientifically important.
Its ethical setting was deeply troubling.
Both belong in the account.
Who Was James B. Hamilton, and What Did He Study?
Hamilton was an American anatomist and hormone researcher associated with Yale University. His 1942 paper was titled “Male Hormone Stimulation Is Prerequisite and an Incitant in Common Baldness” and appeared in the American Journal of Anatomy.
He examined 104 men with testicular insufficiency.
A later peer-reviewed historical analysis reports that Hamilton separated them into groups based on timing:
- 20 whose testicular insufficiency began before puberty
- 34 castrated during adolescence
- 50 castrated after age 20
That distinction was biologically crucial. A follicle that had never received ordinary pubertal androgen stimulation was not equivalent to one that had already spent ten, twenty, or thirty years under it.
Contrary to a frequently repeated version, Hamilton did not inject all 104 participants with testosterone.
He selected twelve men from the prepubertal testicular-insufficiency group for hormone administration.
That smaller experiment supplied the most revealing part of his evidence.
What Happened When Androgen Exposure Was Absent Before Puberty?
Men whose testicular insufficiency began before puberty generally retained a more juvenile frontal hairline and did not develop the usual vertex baldness of adult men.
Those castrated during adolescence could show limited frontotemporal change, which made sense if pubertal androgen exposure had already begun. Extensive crown loss remained uncommon.
When castration occurred after patterned hair loss had started, further progression appeared to slow or stop in many cases. What did not reliably happen was restoration of the original frontal hairline.
Hamilton returned to this issue in a 1960 follow-up involving young men observed for years after castration. His conclusion was blunt: drastic reduction of androgen stimulation offered little remedial value for the return of coarse frontal hair that had already disappeared.
Pause there.
Stopping continued injury and rebuilding a long-miniaturized follicle are not the same biological task. Modern treatment discussions still trip over that distinction.
A medication may preserve hair. A device may thicken some viable hairs. A transplant may relocate resistant follicles. None of those outcomes should be quietly rewritten as “every bald area grows back.”
What Happened When Hamilton Administered Testosterone?
Hamilton administered testosterone to twelve selected men whose testicular insufficiency had begun before puberty.
Four developed typical male-pattern balding.
Eight did not.
The response was linked to family history. The men who developed patterned loss had inherited susceptibility, while testosterone exposure alone did not make every participant bald. In responsive participants, stopping hormone treatment halted progression, and restarting it could restart the process.
That on-off relationship strengthened the causal case.
But the nonresponders may have been even more instructive.
If testosterone automatically produced baldness, all twelve men should have followed roughly the same course. They did not. The follicle’s inherited biology decided whether the hormonal signal became visible loss.
Androgen exposure supplied permission. Susceptible follicles made use of it.
This is why ordinary blood testosterone testing does not diagnose male pattern loss. Two men can have similar circulating hormone values and very different scalps.
What Did the Study Establish?
Hamilton’s research strongly supported three conclusions.
First, ordinary male-pattern balding requires adequate androgen stimulation.
Second, the timing of that stimulation matters. Absence before puberty offers stronger protection than androgen reduction after years of adult exposure.
Third, inherited susceptibility affects whether an androgen-exposed person develops the pattern.
The study did not establish that:
- Balding men have excessive serum testosterone
- Testosterone alone determines severity
- Every person with a family history will become bald
- Castration reverses established frontal loss
- The mechanism is identical in women
- Every type of thinning is androgen-dependent
Hamilton’s wording was careful. Male hormone stimulation was a prerequisite and an incitant.
Not a solitary cause.
What Were the Research Limitations?
By current standards, Hamilton’s investigation lacked many protections and methods expected in clinical research.
There was:
- No randomized allocation
- No placebo group
- No modern blinding
- No computerized hair counting
- No trichoscopic measurement
- No contemporary testosterone or DHT assays
- No prespecified statistical plan resembling a modern trial
- No broad representation across populations
- No reliable basis for extending the findings directly to female pattern hair loss
- No present-day informed-consent structure
Hamilton also did not know that DHT would become a central part of the explanation. The specific role of 5-alpha-reductase and its metabolites was clarified later.
Even so, the temporal evidence was unusually strong for its era. Minimal androgen exposure was followed by minimal male-pattern loss. Testosterone administration triggered loss in susceptible participants. Withdrawal stopped it. Reintroduction restarted it.
Biology left fingerprints.
What Ethical Context Cannot Be Omitted?
Hamilton studied men at the Winfield State Training School in Kansas during the American eugenics era.
Institutionalized people labelled intellectually disabled, mentally ill, sexually deviant, criminal, or socially “unfit” were subjected to sterilization and castration policies intended to control reproduction and behavior. The men available for Hamilton’s study existed within that machinery.
The evidence does not support saying Hamilton personally ordered every castration for baldness research. Many procedures had already occurred within institutional and eugenic systems.
That distinction matters. It does not make the setting ethical.
The surviving reports do not document a consent process remotely comparable with current expectations. Institutionalized participants were vulnerable to coercion, dependency, limited autonomy, and decisions made by authorities over their bodies.
The study also preceded:
- The Nuremberg Code
- The Declaration of Helsinki
- Modern institutional review boards
- Current protections for vulnerable research participants
- Contemporary standards for capacity and voluntary consent
Would the same study be approved now? Not in that form.
A current ethics committee would require a defensible therapeutic purpose, independent consent safeguards, capacity evaluation, participant advocacy, monitoring, withdrawal rights, and proof that an institutional population was not selected simply because it was controllable.
The science retains value. The conditions that supplied the participants remain disturbing.
Useful knowledge can come from an unjust system. Usefulness does not launder the injustice.
What Happens Inside a Genetically Susceptible Hair Follicle?
Testosterone is not a tiny demolition crew marching toward the hairline.
Inside androgen-responsive tissues, some testosterone is converted into DHT. DHT binds androgen receptors in susceptible follicular cells, particularly within the dermal papilla, and alters the messages that regulate hair growth. Over repeated cycles, the affected follicle produces shorter, finer, less pigmented hairs.
The process is gradual.
Often maddeningly so.
How Does Testosterone Become DHT?
Testosterone belongs to a group of steroid hormones called androgens.
In certain tissues, enzymes called 5-alpha-reductases convert testosterone into 5-alpha-dihydrotestosterone, usually shortened to DHT. DHT binds the androgen receptor more avidly than testosterone in several androgen-responsive tissues.
Type I and type II 5-alpha-reductase are the forms most frequently discussed in hair biology and treatment.
- Finasteride preferentially inhibits type II
- Dutasteride inhibits both type I and type II
- Follicular and sebaceous tissues can metabolize androgens locally
- Local activity may differ between scalp regions
This helps explain why a routine blood test can look ordinary while susceptible follicles continue miniaturizing. Serum hormone concentration is only one layer.
It does not directly reveal:
- Enzyme activity in frontal scalp tissue
- Androgen-receptor sensitivity
- Receptor expression
- Local conversion of steroid precursors
- Genetic susceptibility
- Regional differences between follicles
A normal testosterone result therefore does not rule out androgenetic alopecia. A high result does not prove that every shed hair is caused by DHT.
What Happens After DHT Binds the Androgen Receptor?
The dermal papilla is a small cluster of specialized cells near the base of the follicle. It helps regulate the size, cycling behavior, and type of hair produced.
In susceptible scalp follicles, DHT binds androgen receptors within these cells. The activated receptor changes gene transcription and alters signals passed between the dermal papilla and surrounding epithelial structures.
Researchers have implicated several downstream pathways, including:
- Transforming growth factor beta
- Wnt and beta-catenin signaling
- Insulin-like growth factors
- Prostaglandins
- Oxidative signaling
- Extracellular-matrix remodeling
- Perifollicular inflammation
- Fibrotic change
- Cellular-energy metabolism
The evidence for these pathways does not all sit at the same level. Some findings come from cultured cells, animal models, scalp biopsies, or small translational studies. The androgen-receptor link is well supported. The complete sequence from receptor activation to advanced human follicular miniaturization remains partly unresolved.
So no, DHT does not literally clog a follicle, suffocate it, or cut off its blood supply like a villain turning a valve.
It changes cellular instructions.
That is less cinematic. It is also more accurate.
What Does Follicular Miniaturization Mean?
A healthy scalp follicle produces a thick, pigmented terminal hair during its growth phase.
Hair cycling includes:
- Anagen, active growth
- Catagen, brief regression
- Telogen, relative rest
- Exogen, release of the old shaft
- Sometimes a kenogen interval, when the follicle remains temporarily empty
In androgenetic alopecia, susceptible follicles spend progressively less time producing robust terminal hair. The anagen phase shortens. The shaft becomes finer. Growth length decreases. Pigmentation may fade. The interval before replacement hair appears may increase.
One cycle may produce a thick strand.
A later cycle produces a thinner one.
Then a shorter one.
Eventually, the follicle may produce a barely visible vellus-like hair.
This is why someone can lose visible density without finding dramatic clumps in the shower. Coverage depends heavily on shaft diameter, length, curl, pigmentation, and how many robust hairs emerge from each follicular unit.
A small reduction in diameter across thousands of strands can make the scalp look substantially more exposed.
Does the follicle die? That word is often used too freely.
A miniaturized follicle may remain biologically present and continue producing a tiny shaft. Early or moderate miniaturization can sometimes respond to treatment. Longstanding advanced loss becomes less reversible as the follicular apparatus shrinks and structural changes accumulate.
A smooth bald area that has been bare for years is not biologically equivalent to a crown that began thinning six months ago.
Hamilton saw that before anyone could name the mechanism.
Why Does Loss Follow the Temples and Crown?
Scalp follicles keep a strong regional identity.
Follicles around the frontal hairline, temples, mid-scalp, and vertex are more susceptible in genetically predisposed men. Many follicles at the sides and lower back are relatively resistant.
That regional difference involves variations in androgen-receptor biology, steroid-metabolizing enzymes, gene expression, dermal papilla behavior, and local signaling.
The result is the familiar sequence:
- Temple recession
- Frontal hairline retreat
- Mid-scalp thinning
- Crown enlargement
- Eventual joining of frontal and vertex loss
- Relative preservation of a side-and-back rim
That retained rim is sometimes called the Hippocratic wreath.
The Hamilton-Norwood scale grades common male patterns from minimal recession through extensive loss. It is useful for description and monitoring. It does not diagnose the cause on its own.
Why not?
Because frontal fibrosing alopecia, traction, diffuse unpatterned alopecia, inflammatory disease, and combined conditions can imitate parts of the pattern.
The donor region used in hair transplantation is also relatively resistant, not magically immune. Some people develop thinning or miniaturization within areas once assumed to be permanently safe.
Why Do Some Men Lose Hair While Others Do Not?
Androgenetic alopecia is polygenic.
The androgen-receptor gene on the X chromosome is an important contributor, but it is not the lone “baldness gene.” Large genomic studies have identified hundreds of associated genetic signals, many on autosomes inherited from either parent.
So the famous maternal-grandfather rule is, at best, a sliver of the inheritance pattern wearing a very confident hat.
A father can pass susceptibility to his son through autosomal genes.
A mother can pass relevant variants too.
Several branches of a family may contribute smaller effects.
Someone can develop pattern loss without an obviously bald relative because:
- Relatives inherited different combinations
- Severity differed
- Onset occurred later
- Female relatives expressed the tendency differently
- Family history is incomplete
- Susceptibility came from several sides
- The trait did not become visually obvious in earlier generations
Brothers can also follow different courses because they do not inherit identical genetic combinations.
Even identical twins may vary somewhat in timing or severity. Genes shape probability. Age, health, endocrine exposure, medications, and other biological influences shape expression.
Commercial genetic testing can estimate risk imperfectly. It cannot reliably tell one person the exact year their crown will thin, how far recession will progress, or whether a specific treatment will work.
The scalp has not signed that contract.
Why Can DHT Support Beard Growth but Reduce Scalp Hair?
Because follicles from different body sites respond differently to the same hormone.
Androgens help convert fine facial hairs into coarse beard hairs during puberty. They also support growth in axillary and pubic regions.
Yet in susceptible frontal scalp follicles, androgen signaling promotes miniaturization.
This is called the androgen paradox, though the biology is less contradictory once regional follicular identity is considered. Beard dermal papilla cells and frontal scalp dermal papilla cells send different downstream signals after androgen-receptor activation.
A thick beard therefore does not reliably predict severe scalp loss. Neither does chest hair, libido, fertility, muscle size, or any other folk measurement of “high testosterone.”
A thick beard is not a home DHT blood test wearing a chin strap.
Does the Same Explanation Apply Identically to Women and Transgender Patients?
No.
Female pattern hair loss involves miniaturization, usually across the central scalp with relative preservation of the frontal hairline. Most affected women do not have clearly elevated circulating androgens, and the biological contribution of androgens appears less uniform than in male pattern loss.
Hormonal assessment becomes more relevant when thinning occurs alongside:
- Increased facial or body hair
- Persistent acne
- Irregular menstrual periods
- Infertility
- Voice deepening
- Rapid muscle change
- Other signs of virilization
Those features may prompt evaluation for polycystic ovary syndrome, medication effects, adrenal conditions, or, rarely, an androgen-secreting tumor.
Gender-affirming testosterone can initiate or accelerate androgenetic alopecia in susceptible transgender men. It does not happen to everyone, and it may appear years after testosterone begins.
Treatment should respect the person’s priorities. Stopping testosterone may be unwanted and unnecessary. Finasteride may help scalp hair but could influence some desired androgen-dependent changes. A 2025 three-person case series reported hair improvement with finasteride, while two participants resumed menstruation, a reminder that the evidence is small and the broader hormonal consequences matter.
For transgender women, estrogen and androgen-lowering treatment may slow progression or improve recently miniaturized hair. It should not be promised to recreate a long-receded hairline.
Pregnancy potential, fertility goals, anatomy, medication risks, and gender identity cannot be inferred from one another.
Care needs an actual conversation.
Is Your Hair Loss Actually Androgenetic Alopecia?
A slowly receding hairline may be androgenetic alopecia.
It may also be traction, frontal fibrosing alopecia, alopecia areata, breakage, telogen effluvium layered over pattern loss, or something else entirely.
The ancient eunuch clue explains one biological process. It cannot diagnose a reader from a bathroom-mirror inspection, especially when the overhead bulb seems personally committed to making every crown look thin.
What Does Male Androgenetic Alopecia Usually Look Like?
Male pattern loss generally begins gradually after puberty.
Common signs include:
- Increasing temple recession
- A hairline that continues moving backward
- Finer hairs along the frontal edge
- Expanding crown visibility
- Reduced mid-scalp density
- Greater contrast between hair at the top and hair at the sides
- Progressive change over months or years
The scalp skin usually appears normal. Severe redness, crusting, pustules, intense pain, smooth round patches, or disappearance of follicular openings is not the usual presentation. (American Academy of Dermatology Association, n.d.)
A mature hairline is not automatically active baldness. Many adult men develop modest, symmetric recession from the juvenile hairline without rapid ongoing miniaturization.
One photograph cannot always separate the two.
Progress matters. Shaft-diameter variation matters. Family history helps. Trichoscopy may settle what ordinary lighting cannot.
Is Shedding the Same as Pattern Thinning?
No.
Shedding describes hairs being released from follicles.
Thinning describes reduced visible coverage.
Breakage describes shafts snapping above the scalp.
Miniaturization describes a follicle producing progressively finer hair.
These can overlap, which is where things become messy.
A person with androgenetic alopecia may notice increased shedding during some periods. Another person may miniaturize slowly without a dramatic change in the shower drain. A third may develop telogen effluvium after illness, suddenly shedding long terminal hairs and revealing pattern loss that had previously been subtle.
One person watches the crown become more visible over two years.
Another fills the brush after surgery.
Another has short snapped hairs from repeated chemical and heat exposure.
The outcomes may all be described casually as “hair loss,” but the biological problems differ.
What Conditions Can Resemble DHT-Related Loss?
|
Condition |
Common clue |
How it differs from typical male pattern loss |
|
Telogen effluvium |
Diffuse shedding after illness, fever, surgery, childbirth, weight loss, dietary restriction, medication change, or marked strain |
Usually affects the scalp more diffusely and often follows a trigger by several weeks or months |
|
Alopecia areata |
Sudden smooth patches, eyebrow loss, beard patches, nail changes, or diffuse autoimmune loss |
Not driven by the ordinary male DHT-sensitive pattern |
|
Traction alopecia |
Loss in areas repeatedly pulled by hairstyles, extensions, attachments, headwear, or adhesives |
Distribution follows mechanical tension and can scar when longstanding |
|
Tinea capitis |
Scale, broken hairs, tenderness, inflammation, or swollen lymph nodes |
Fungal infection requires antifungal treatment |
|
Trichotillomania |
Irregular patches containing broken hairs of several lengths |
Caused by recurrent pulling rather than follicular miniaturization |
|
Frontal fibrosing alopecia |
Recession with smooth skin, eyebrow loss, perifollicular scale, or symptoms |
A scarring inflammatory alopecia that can permanently destroy follicles |
|
Lichen planopilaris |
Itching, burning, pain, perifollicular redness, or scale |
Scarring disease needing inflammation-focused medical care |
|
Central centrifugal cicatricial alopecia |
Central or crown thinning, breakage, tenderness, burning, or scarring, particularly in Black women |
Inflammatory scarring alopecia, not ordinary androgenetic miniaturization |
|
Hair-shaft breakage |
Short uneven strands after bleach, relaxer, heat, friction, or rough handling |
Shaft damage may occur while the follicle remains intact |
|
Nutritional or endocrine shedding |
Diffuse loss with anemia, dietary restriction, thyroid symptoms, or systemic illness |
Requires targeted evaluation rather than assumed DHT treatment |
Several conditions can occur together.
A man can have androgenetic alopecia and telogen effluvium.
A woman can have female pattern loss and traction.
A person can have seborrheic dermatitis on a scalp that is also miniaturizing.
The presence of one diagnosis does not politely evict all the others.
How Is Androgenetic Alopecia Diagnosed?
Diagnosis usually begins with:
- Timing
- Pattern
- Rate of progression
- Family history from both sides
- Recent illness, surgery, fever, or weight change
- Diet
- Medications and supplements
- Hair-care practices
- Scalp symptoms
- Examination of the entire scalp
Trichoscopy gives a magnified view of hair shafts, follicular openings, pigment, and surrounding skin.
A 2024 systematic review covering 34 studies found that the most frequently reported trichoscopic findings included hair-diameter variability, increased vellus hairs, and the peripilar sign. The authors reported those features in approximately 94%, 66%, and 43% of included patients, respectively, though methods and populations varied across studies.
Blood tests are not always needed in a classic gradually patterned male presentation.
Targeted testing may be considered when loss is:
- Diffuse
- Sudden
- Rapid
- Accompanied by systemic symptoms
- Occurring with dietary restriction
- Associated with endocrine signs
- Atypical for age or pattern
Depending on history, a clinician may consider a complete blood count, ferritin or iron studies, thyroid testing, nutrient testing, or hormonal evaluation.
Routine serum DHT testing rarely settles a typical diagnosis.
A scalp biopsy may be used when scarring, inflammation, mixed disease, or an uncertain pattern remains possible.
When Should Someone Seek Prompt Medical Assessment?
Arrange medical assessment when hair loss is:
- Sudden
- Rapidly expanding
- Occurring in clumps
- Smoothly patchy
- Painful, burning, or intensely itchy
- Accompanied by crust, pus, bleeding, or marked scale
- Affecting eyebrows or eyelashes
- Leaving shiny skin with fewer follicular openings
- Beginning in childhood
- Following a new medicine
- Accompanied by fatigue, weight change, menstrual disturbance, or systemic illness
- Occurring with rapid signs of androgen excess
- Progressing despite treatment
A board-certified dermatologist is best placed to diagnose inflammatory, autoimmune, infectious, scarring, and medically complicated forms of loss.
A qualified trichologist can support scalp assessment, monitoring, hair-care planning, and education. Prescribing, biopsy, and systemic medical investigation belong within the appropriate licensed scope.
A stubborn patch deserves a diagnosis before it receives six serums and a motivational speech.
How Did the Ancient Clue Shape Hair-Loss Treatment Today?
Modern treatment does not try to reproduce the full hormonal consequences of castration.
Instead, it may:
- Reduce DHT production
- Support follicles through a non-androgen pathway
- Apply light-based cellular stimulation
- Use antiandrogens in selected patients
- Deliver procedural growth signals
- Move relatively resistant follicles surgically
- Improve appearance without changing biology
- Or leave the hair untreated
That last option is medically valid too.
Hair loss can be treated. It does not have to be.
What Can Treatment Realistically Achieve?
Treatment may:
- Slow further progression
- Stabilize density
- Thicken some miniaturized hairs
- Increase average hair counts
- Improve coverage
- Reduce shedding in selected cases
- Maintain existing hair
- Provide surgical redistribution
It may not:
- Restore every receded temple
- Rebuild follicles absent for many years
- Guarantee visible regrowth
- Work equally for everyone
- Continue working after it is stopped
- Correct the wrong diagnosis
Stabilization matters.
A person who has been losing density each year may judge “no further change” as disappointing beside a dramatic advertisement. Biologically, keeping the remaining terminal hairs may be the most valuable outcome available.
Where Does Laser Phototherapy Fit?
Laser Phototherapy, or LPT, is a non-ablative form of photobiomodulation.
It does not cut, burn, remove, or transplant tissue. It also does not lower testosterone or block DHT.
Proposed biological effects include changes in mitochondrial signaling, cellular-energy production, nitric-oxide activity, oxidative signaling, inflammatory mediators, and hair-cycle regulation.
A systematic review and meta-analysis of seven double-blind randomized controlled trials found that FDA-cleared home-use low-level light or laser devices produced a statistically significant increase in hair density compared with sham devices. The authors also emphasized the need for longer follow-up, research in more advanced loss, combination studies, and direct comparisons between device designs and energy sources.
Devices vary in:
- Wavelength
- Coherence
- Irradiance
- Fluence
- Treatment duration
- Diode number
- Coverage
- Distance from scalp
- Schedule
- Clinical evidence
- User adherence
A positive trial involving one device cannot automatically be assigned to every red-light cap, comb, panel, or helmet.
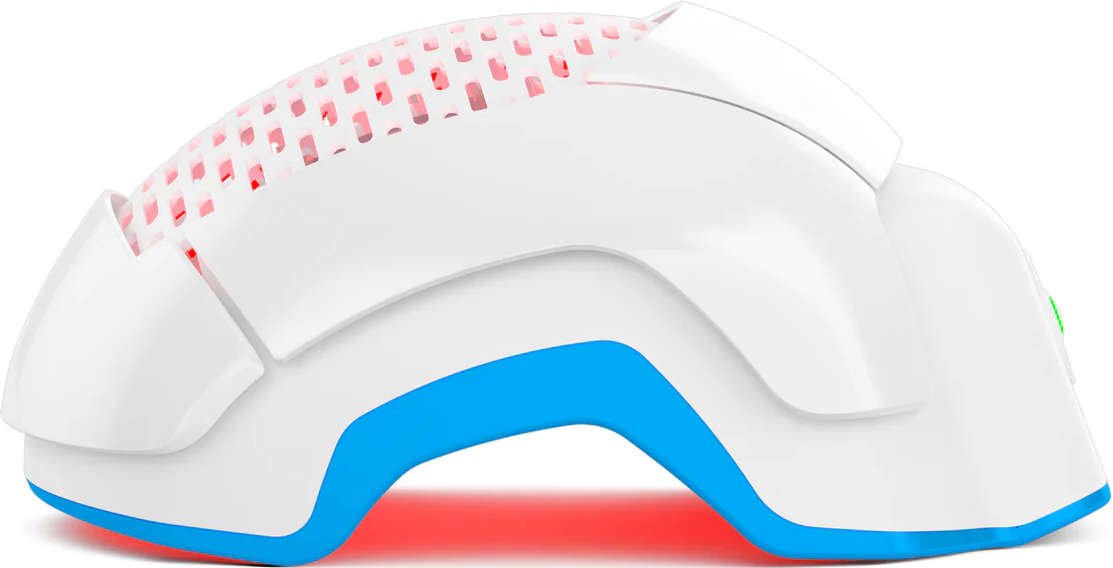
The Theradome LH80 PRO is a wearable helmet containing 80 coherent light diodes intended to deliver treatment across the scalp during a twenty-minute session. FDA records show:
- Prescription clearance for specified female androgenetic alopecia patterns in March 2012
- Women’s over-the-counter clearance in June 2013
- Over-the-counter clearance for specified male and female androgenetic alopecia patterns in January 2018
The 2018 indication covers men with Norwood-Hamilton IIa to V patterns and women with specified Ludwig-Savin classifications, within Fitzpatrick skin types I to IV.
LPT may be considered:
- By someone with diagnosed androgenetic alopecia who prefers a non-drug approach
- When medication is unsuitable or unwanted
- Alongside clinician-directed treatment
- As part of a plan where long-term adherence is realistic
What Other Treatments May Be Considered?
Dutasteride inhibits type I and type II 5-alpha-reductase and generally suppresses DHT more strongly than finasteride. Network meta-analyses have ranked oral dutasteride 0.5 mg highly for average hair-density outcomes in men. It is not FDA-approved for hair loss in the United States and is used off-label. Its long half-life, sexual and reproductive considerations, PSA effects, and pregnancy exposure risks require proper discussion.
Spironolactone is used off-label in selected women, particularly where androgen excess or androgen sensitivity is suspected. It can lower blood pressure, increase potassium, alter menstruation, cause breast tenderness, and create pregnancy-related concerns.
Platelet-rich plasma, or PRP, involves injecting a platelet concentrate prepared from the patient’s blood. Reviews suggest benefit for hair density in some patients, but preparation methods, platelet concentration, activation, injection technique, schedules, and maintenance vary considerably.
Microneedling creates controlled microinjury and may improve growth signaling or topical-drug delivery. Evidence is stronger as an adjunct than as a stand-alone treatment. Infection, irritation, and scarring are possible when technique is poor or inflammatory scalp disease has not been ruled out.
Hair transplantation relocates follicles from a relatively resistant donor region. Follicles are redistributed, not multiplied. Native susceptible hair can continue thinning afterward.
Cosmetic approaches include fibers, scalp concealers, scalp micropigmentation, hair systems, wigs, and styling changes.
And then there is shaving the head, wearing the hair short, or doing nothing.
No treatment is also a decision.
Which Treatments Remain Investigational?
Research is examining:
- Topical androgen-receptor antagonists
- Androgen-receptor degraders
- Wnt-pathway agents
- Follicular stem-cell activation
- Exosomes
- Stem-cell-derived preparations
- Extracellular vesicles
- New prostaglandin targets
- Metabolic and mitochondrial pathways
Early laboratory work can be compelling. Small uncontrolled clinical studies can be intriguing too.
Neither is the same as a proven routine treatment.
Exosome and stem-cell offerings vary in source material, processing, purity, dose, storage, sterility, regulatory status, and active contents. Long-term safety and durability remain uncertain.
A plausible mechanism deserves further study.
It does not deserve an automatic credit-card number.
How Long Should Treatment Be Given Before Judging It?
Hair biology is slow.
A rough assessment timeline looks like this:
First few weeks: Visible conclusions are premature. Irritation or tolerability problems may appear early.
Two to three months: Shedding can fluctuate. Finasteride may only be beginning its biological effect. Minoxidil users may notice a temporary shed.
Four to six months: Early stabilization or subtle thickening may become visible in some responders.
Six to twelve months: This is a more useful comparison window for photographs, density, and shaft quality.
Beyond twelve months: Maintenance, long-term tolerability, and whether continued treatment fits real life become clearer.
Use consistent photographs:
- Same room
- Same lighting
- Same camera
- Same angle
- Same hair length where possible
- Same wet-or-dry condition
- Same parting
- No fibers or concealer
Daily mirror checks provide a great deal of emotion and remarkably little usable data.
And the callback to Hamilton remains unavoidable: reducing a continuing stimulus can preserve hair more readily than it can rebuild an area that has been bare for years.
Conclusion
Eunuchs can lose hair. What profound early androgen deficiency largely prevented was classic male pattern baldness.
The Hippocratic tradition recorded the pattern. Aristotle tried to explain it. Hamilton later showed that androgen exposure and inherited susceptibility had to meet inside the same scalp. Modern research added DHT, 5-alpha-reductase, androgen receptors, genetics, and follicular miniaturization.
That ancient clue explains androgenetic alopecia, not every thinning head.
When the pattern is gradual and familiar, treatment may preserve hair or thicken viable follicles. When loss is sudden, painful, patchy, inflamed, or unclear, diagnosis comes first.
Modern care offers medication, LPT, procedures, cosmetic options, surgery, and the valid choice not to treat.
The ancient physicians saw the pattern. Medicine eventually supplied the missing biology and, thankfully, far less drastic choices.